

“A person may have withdrawal symptoms after stopping or significantly decreasing heavy or long-term cannabis use, even if they don’t have cannabis use disorder.”
National Institute on Drug Abuse, “Cannabis (Marijuana)” (2024)
We almost left this page the way it was. The first version, from 2022, is Sai’s own account of quitting weed, relapses included, and a real story like that is hard to improve on. But it also told readers to do one last big session before quitting, and it leaned on scary health claims more than the research does. So we kept the story and rebuilt everything around it. Which part of quitting are you most worried about?
Maybe you know the evening that brings people here. Work is done, the room goes quiet, and the hour that always ended with a joint is just sitting there, empty. You are irritable for no reason. You cannot fall asleep, and when you do, the dreams are strange. You have told yourself “this is the last week” more than once.
Here is something worth knowing before you start. When researchers led by Alan Budney watched heavy users stop for 45 days, withdrawal usually began within the first three days, peaked between days two and six, and mostly faded within four to fourteen days. It was a small study, but it means the hardest stretch is shorter than it feels from the inside. The real work is what to do with the rooms in your day that weed used to fill. This guide covers what to expect, why people go back, five steps to get through it, and exactly when to get medical help.
The short version
What to expect: irritability, anxiety, restlessness, poor sleep, strange dreams, low appetite and cravings. In one study, symptoms began within three days, peaked around days two to six, and mostly eased within two weeks.
Is weed addictive? NIDA estimates that 22% to 30% of people who use cannabis have cannabis use disorder. You can also get withdrawal without it.
Why people go back: most quit attempts start with no preparation, and sleep problems are thought to be the symptom most linked to relapse.
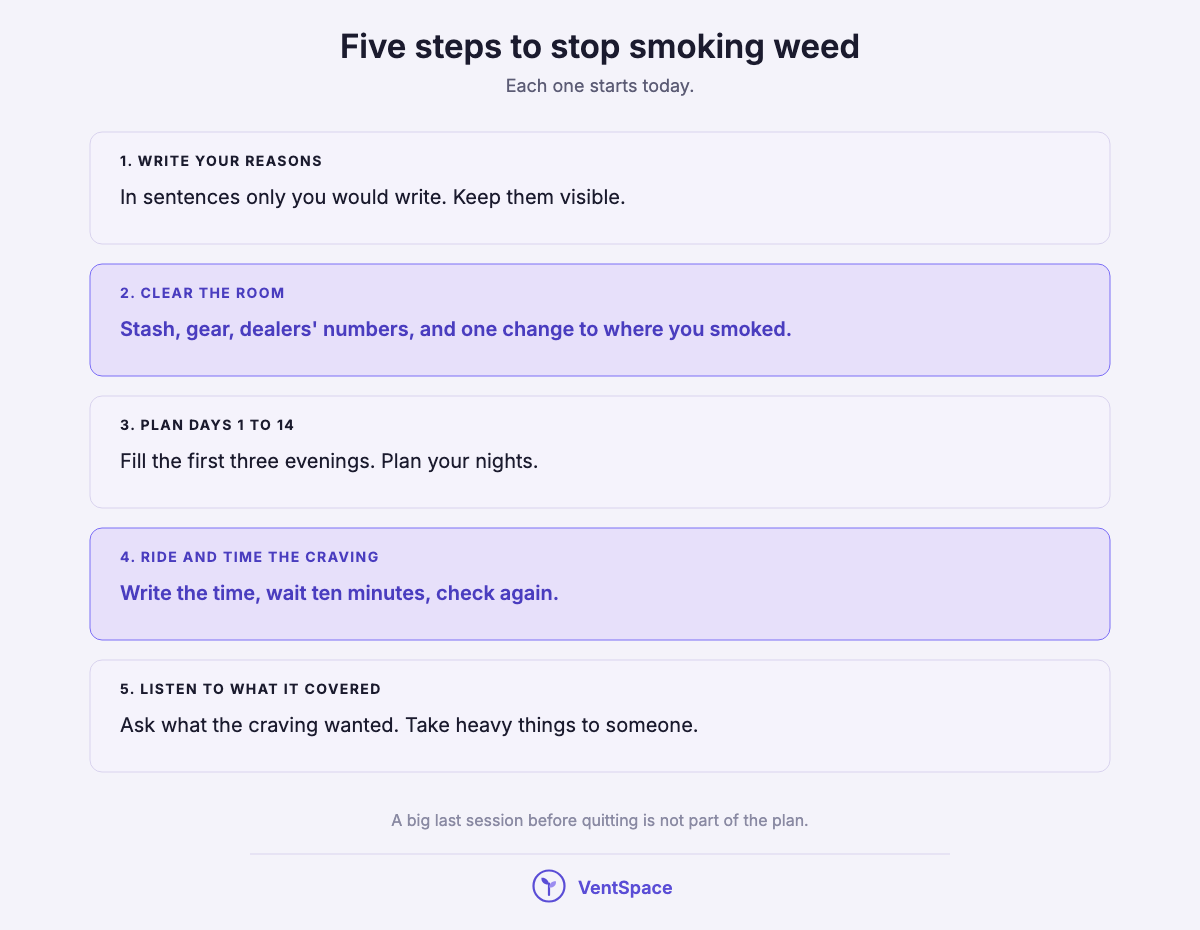
The five steps: write your reasons, clear the room, plan days 1 to 14 before day 1, ride and time the craving, and listen to what it was covering.
Get medical help for chest pain (call 911), repeated vomiting, pregnancy, or if you also use other substances or have a mental health condition.
If you’re in crisis or thinking about harming yourself, please contact the 988 Suicide & Crisis Lifeline now (US, call or text 988), or find a line in your country at findahelpline.com. If you have chest pain, call 911, even if you are not sure it is serious. For help finding treatment for cannabis use, the SAMHSA National Helpline is 1-800-662-HELP (4357).

What happens when you quit weed
“Withdrawal symptoms may include anger, irritability, aggression, feeling nervous or anxious, restlessness, decreased appetite or weight, depression, insomnia, experiencing strange or unsettling dreams, headaches, sweating, abdominal pain, and tremor.”
National Institute on Drug Abuse, “Cannabis (Marijuana)” (2024)
When you stop after heavy or long-term use, you may get a few days to two weeks of irritability, anxiety, restlessness, poor sleep, low appetite, strange dreams and cravings. For most people it is uncomfortable rather than dangerous. A 2017 review describes the symptoms as mainly “of light to moderate intensity,” usually manageable without a hospital stay.
The day ranges come from one careful study. Budney and colleagues followed 18 heavy users through five days of smoking as usual and then 45 days without. Here is what they saw:
| When | What the study saw | What helps |
|---|---|---|
| Days 1 to 3 | Symptoms usually start | Have the first three days planned before you begin |
| Days 2 to 6 | Symptoms peak: irritability, anger, anxiety, restlessness, sleep problems, low appetite, stomach pain, shakiness | Keep the days full and the evenings protected |
| Days 4 to 14 | Most effects fade | Expect a few rough days, not every day |
| Later | Strange dreams can show up later than the rest, a 2017 review notes | Treat dreams as a symptom, not a sign of failure |
The “What helps” column is our advice, built from the steps below. The study was small and old, so take the days as a rough map rather than a promise.
How many people get withdrawal at all? It depends on who you ask. NIDA cites one estimate that 12.1% of people who frequently use cannabis experience withdrawal. A 2020 meta-analysis of 47 studies and 23,518 people found 47% of regular or dependent users did, ranging from 17% in general population samples to 54% in outpatient and 87% in inpatient treatment samples. Daily use was linked to higher rates. Women in one review reported stronger withdrawal, including nausea and stomach pain.
From Sai, who writes this site
I have felt weirdness in my stomach every time I was on a break from weed. It might not be the same for everyone, but your body is adjusting to a new normal. I had dreams about smoking too. They did not push me to go back. I learned to laugh them off and get on with my day.
If your body does not settle, or something feels more than uncomfortable, do not judge it from a blog. Chest pain, repeated vomiting, or symptoms that scare you are a reason to get checked, and the help section below says where.
Quick Summary
Q: What are the symptoms of weed withdrawal and how long do they last?
A: Common symptoms are irritability, anxiety, restlessness, poor sleep, low appetite, strange dreams, stomach pain and cravings. In one study of heavy users, they began within three days, peaked between days two and six, and mostly faded within four to fourteen days.
Insight: why most people can do this at home
“Several lines of evidence from animal and human studies indicate that cessation from long-term and regular cannabis use precipitates a specific withdrawal syndrome with mainly mood and behavioral symptoms of light to moderate intensity, which can usually be treated in an outpatient setting.” Udo Bonnet and Ulrich Preuss, Substance Abuse and Rehabilitation, 2017.
Is weed addictive?
“Studies have estimated that 22% to 30% of people who use cannabis have the disorder.”
National Institute on Drug Abuse, “Cannabis (Marijuana)” (2024)
Yes, it can be. Doctors call it cannabis use disorder, which the DSM-5 defines as “a pattern of use that leads to clinically significant impairment or distress.” NIDA estimates that between 22% and 30% of people who use cannabis have it. Most people who use do not develop it, which may be part of why the idea that weed is not addictive has lasted so long.
What raises the risk? According to NIDA, “The strongest predictor of cannabis use disorder is how often someone uses it.” A family history of drug use and how long you have been using also play a role, and starting young raises the chance of developing the disorder later. Potency matters too. Between 1995 and 2022, the THC strength of illegal cannabis seized by law enforcement quadrupled, from 3.96% to 16.14%, and some dispensary products are above 40%.
Clinicians diagnose the disorder using a list of 11 symptoms over a 12-month period, such as using more than you meant to, failing to cut down, craving, giving up activities you cared about, and withdrawal when you stop. That list is for a clinician, not a quiz to score yourself on. If you are reading this page because you have tried to stop and could not, that alone is a good reason to talk to someone.
And you do not need a diagnosis to have a hard time stopping. As the quote at the top of this page says, withdrawal can happen even without the disorder. Does it matter what you call it, if you already know you want to stop?
From Sai, who writes this site
Honestly, quitting weed was a long process, full of relapses and lessons from those relapses. I would find the strength to get through the first few days, and then something in my life would pull me back.
Quick Summary
Q: Is weed addictive?
A: It can be. NIDA estimates that 22% to 30% of people who use cannabis have cannabis use disorder, and how often someone uses is the strongest predictor. Withdrawal can also happen in people who do not have the disorder.
Insight: is what I feel normal?
“The overall pooled prevalence of CWS was 47% (6469 of 23 518) (95% CI, 41%-52%), with significant heterogeneity between estimates (I2 = 99.2%).” And: “These findings suggest that cannabis withdrawal syndrome appears to be prevalent among regular users of cannabis.” Anees Bahji and colleagues, JAMA Network Open, 2020. (CWS is cannabis withdrawal syndrome.)
Why people go back
Most quit attempts are short, most start without a plan, and poor sleep is thought to be the withdrawal symptom most tied to going back. None of that means you will fail. It means the attempt needs more preparation than willpower.
A study by John Hughes and colleagues followed 193 daily users trying to stop or cut down on their own, with a phone check-in every morning for three months. Their attempts were often short-lived, few reached long-term abstinence, and most did not prepare before they started. There was good news in the same data: more days without cannabis, or of deliberately cutting down, predicted a bigger drop in dependence, and coping well during a quit attempt predicted a longer one. Every day counts, even the ones before a slip.
Sleep is the other thing to plan for. The 2017 review notes that sleep difficulty is the withdrawal symptom “assumed to be most associated with relapse.” If your nights were built around weed, plan for the first week of bad sleep before it arrives.
From Sai, who writes this site
I buried myself in work and the gym to get away from the cravings, and it worked. I was off it for months. I was happy, sleeping and eating well. Then a strong trigger from my past brought back a lot of thoughts about smoking. I did not give up straight away, but once I started wondering and craving, I broke. Even after that relapse, I was not back where I started. I could still sleep and work normally, and I used my fear of the insomnia I had when I was smoking every day to get off it again.
What do you think was underneath the last time you went back? Was it the people, the hour, the mood, or something older? The steps below are built to answer exactly that.
Quick Summary
Q: Why is it so hard to quit weed?
A: Most quit attempts are short and start without preparation, withdrawal peaks in the first week, and poor sleep is thought to be the symptom most linked to relapse. Days without weed and good coping during an attempt are both linked to better outcomes.
Insight: the shape of withdrawal
“A withdrawal pattern was observed for aggression, anger, anxiety, decreased appetite, decreased body weight, irritability, restlessness, shakiness, sleep problems, and stomach pain. Onset typically occurred between Days 1-3, peak effects between Days 2-6, and most effects lasted 4-14 days. The magnitude and time course of these effects appeared comparable to tobacco and other withdrawal syndromes.” Alan Budney and colleagues, Journal of Abnormal Psychology, 2003.
So how do you get through the first two weeks?
How to stop smoking weed in five steps
“Accumulate all the possible circumstances which shall re-enforce the right motives; put yourself assiduously in conditions that encourage the new way; make engagements incompatible with the old; take a public pledge, if the case allows; in short, envelop your resolution with every aid you know.”
William James, The Principles of Psychology (1890), Chapter IV, “Habit”
Each step starts with something you can do today. Do them in order before your quit day, then come back to steps 4 and 5 whenever a craving hits.
1. Write your reasons in your own words
Take a sheet of paper and write down why you want to stop, in sentences only you would write. Not “health” but “I want to stop waking up foggy before my 9 a.m. meeting.” Keep it in your wallet or as your phone’s lock screen.
This is the core of motivational enhancement therapy, one of the treatments with the most consistent support in a 2016 Cochrane review of cannabis treatments, especially combined with cognitive behavioral therapy. You are doing a small version of it on your own.
From Sai, who writes this site
My reasons were losing track of who I was and what made me happy, my productivity, my health and the way I looked, the past I was covering up instead of dealing with, and the friendships I had let slide. Trust me, the pain of regret is way greater than the pain of withdrawal.
- What has weed cost you this month, in money, time or mornings?
- What did you used to enjoy that does not excite you now?
- Who would notice first if you stopped?
- What do you want your evenings to look like a month from now?
You do not need a dramatic reason. A quiet one you believe is enough.
2. Clear the room
Before your quit day, remove what you can of the cues. Throw out or give away what you have left and the gear. Delete or block your dealers’ numbers. Tell your smoking friends you are taking a break, in one sentence. And change the place you used to smoke in, even a little.
That last one is Sai’s, and it is where this page’s idea of the empty room comes from. If the habit lives in a room, the room has to change.
From Sai, who writes this site
My triggers were friends who smoked with me, dealers, and places. I stayed away from those friends for the first few months and blocked every dealer, because if someone called and asked if I needed some, I might break. If you always smoked in your room, redecorate it so it does not have the same feel.
- Who do you usually smoke with, and where?
- Whose number would make it easiest to slip?
- What could you move, change or throw out in that room today?
- What will you say when a friend offers?
One thing we do not recommend from the old version of this page is a big last session before quitting. A 2017 review found that withdrawal severity depends on how much cannabis someone was using before stopping, and the old page itself warned that a big session might increase withdrawal symptoms in the first three days. Sai’s more useful lesson was the morning after: when friends offered what was left, he said no, and in his experience that first no made the next ones easier.
3. Plan days 1 to 14 before day 1
Open your calendar and fill the first three evenings with something specific, at the hour you would usually smoke: a class, the gym, a friend who does not smoke, a long walk with a podcast. Then sketch the rest of the first two weeks more loosely.
This step matters because in Hughes’s study most people did not prepare before a quit attempt, and Budney’s data puts the peak of withdrawal at days two to six. Plan for low appetite with small, easy meals, and plan your nights: a fixed time to put the phone away, and something to do if you cannot sleep.
- What hour of the day will be hardest, and what will you be doing then?
- Who can you see in the first three days?
- What will you do at 1 a.m. if you are wide awake?
- What easy food can you keep in for days you have no appetite?
If the plan falls apart on day three, that is fine. Make a smaller plan for day four.
4. Ride the craving, and time it
When a craving hits, look at the clock and write down the time. Then do something with your hands for ten minutes and check again. You are finding out how long yours lasts.
Sai’s old advice was to study your cravings: how long they last, whether they are stronger when you are idle, whether they get louder around certain people and places. That is close to a technique called urge surfing. In a 2009 trial with 123 student cigarette smokers, Sarah Bowen and Alan Marlatt found that a short mindfulness instruction did not reduce the urges, but the people who learned it smoked fewer cigarettes over the next week. It was about tobacco, not cannabis, so treat it as a reasonable thing to try.
- What time did the craving start, and when did it ease?
- Were you idle, tired, or with someone you used to smoke with?
- What excuse did your mind offer this time?
- What did you do instead, and did it help?
Your mind will offer good excuses: a birthday next week, a stressful day, “just once.” Write the excuse down next to the time. Seeing it on paper makes it easier to look at.
5. Listen to what it was covering
Once the worst days pass, ask the craving what it wanted. Sai’s view was that distraction gets you through the peak, but if you only run from the feelings under the habit, they come back later and pull you with them.
From Sai, who writes this site
I used to journal a lot and be in touch with my feelings, but once I started smoking I stopped most of my mental health routines. Running away from problems was one reason I relapsed after a long break.
These were Sai’s own questions for listening to a craving:
- Why do I have the urge to smoke right now?
- Why did I start smoking in the first place?
- What drove me back then, and what drives me now?
- What do I feel when I smoke?
- What am I afraid of, and why am I trying to quit?
Some of the answers may be hard. If they bring up something you cannot carry alone, that is exactly what a therapist is for. Rebuilding the rooms takes time, and our guide to self-awareness is a good next read for the “who am I without it” question.
When to get medical help or treatment
“Psychosocial intervention was shown, in comparison with minimal treatment controls, to reduce frequency of use and severity of dependence in a fairly durable manner, at least in the short term.”
Peter Gates and colleagues, Cochrane Database of Systematic Reviews (2016)
Get medical help straight away for chest pain or repeated vomiting, and talk to a doctor before or while you quit if you are pregnant, use other substances heavily, or have a mental or physical health condition. For everyone else, treatment is worth considering if you have tried on your own and keep going back.
Chest pain: call 911. The National Heart, Lung, and Blood Institute advises calling “for emergency medical care, even if you are not sure that you’re having a heart attack.” NIDA notes that cannabis can raise heart rate and blood pressure right after use and that some research links long-term use with heart problems, though more research is needed.
Repeated vomiting. Cannabinoid hyperemesis syndrome is nausea, vomiting and abdominal pain after long-term, heavy cannabis use. NIDA says it “can recur and often requires medical attention.”
Pregnancy. NIDA says cannabis use during pregnancy may harm a baby’s health after birth, including lower birth weight and preterm birth. Your doctor or midwife can help you stop.
Other conditions or heavy use. A 2017 review notes that having other mental or physical health conditions, severe cannabis use disorder, or low social functioning “may require an inpatient treatment.” If you have a history of psychosis, or you also drink or use other drugs heavily, talk to a doctor before you quit on your own.
Low mood that lasts. If you feel down most of the day, nearly every day, for two weeks or more, the National Institute of Mental Health advises talking to a health care provider.
Treatment works, and it is not a last resort. NIDA lists cognitive behavioral therapy, motivational enhancement therapy and contingency management (incentives for staying off cannabis) as treatments that can be effective. A Cochrane review of 23 trials with 4,045 people found that these talking treatments, usually about seven sessions over about 12 weeks, cut how often people used and how dependent they were. It was honest about the limit too: the rate of full abstinence was low, though comparable with treatment for other substances. There are no FDA-approved medications for cannabis use disorder or for withdrawal, according to NIDA.
For referrals to treatment in the US, NIDA directs people to the SAMHSA National Helpline at 1-800-662-HELP (4357) or FindTreatment.gov. If you are unsure whether you need therapy or just someone to talk to, our guide on whether you need therapy can help you decide.
Quick Summary
Q: When should I see a doctor about quitting weed?
A: Call 911 for chest pain. Get medical help for repeated vomiting. See a doctor before or while quitting if you are pregnant, use other substances heavily, or have a mental or physical health condition. Therapy such as CBT and motivational enhancement therapy can help, and the SAMHSA National Helpline (1-800-662-4357) gives treatment referrals.
Insight: who needs more than a home plan
“The CWS severity is dependent on the amount of cannabis used pre-cessation, gender, and heritable and several environmental factors. Therefore, naturalistic severity of CWS highly varies. Women reported a stronger CWS than men including physical symptoms, such as nausea and stomach pain. Comorbidity with mental or somatic disorders, severe CUD, and low social functioning may require an inpatient treatment (preferably qualified detox) and post-acute rehabilitation.” Udo Bonnet and Ulrich Preuss, Substance Abuse and Rehabilitation, 2017.

Pulling it all together
The five steps make one path out of the empty room.
First, write your reasons in your own words and keep them where you will see them. Do it tonight.
Then, clear the room: the stash, the gear, the dealers’ numbers, and one change to the place you smoked.
Before day 1, fill the first three evenings at the hour you would usually smoke, and plan your nights.
When a craving hits, write down the time, do something with your hands for ten minutes, and check again.
Once the worst days pass, ask the craving what it was covering, and take anything heavy to someone who can help.
Questions people ask
How long does weed withdrawal last?
In one study of heavy users, symptoms began within three days, peaked between days two and six, and mostly faded within four to fourteen days. Strange dreams can come later than the rest. It was a small study, and how hard withdrawal hits varies with how much you used.
Is weed not addictive?
That is a common belief, but it is not accurate. NIDA estimates that 22% to 30% of people who use cannabis have cannabis use disorder, and frequent use is the strongest predictor. Many people who use never develop it, which may be part of why the myth survives.
Should I quit cold turkey or cut down first?
There is no proven schedule either way. In one study of daily users, more days without cannabis or of deliberately cutting down both predicted a bigger drop in dependence. If you use heavily every day, use other substances, or have a health condition, ask a doctor to help you plan.
Why can’t I sleep after quitting weed?
Sleep difficulty is one of the most common withdrawal symptoms, and it tends to peak in the first week. Plan your nights before you quit. If sleep stays poor beyond the first couple of weeks, talk to a doctor rather than reaching for something to knock you out.
Is chest pain after quitting weed normal?
Do not assume it is. Chest pain is a reason to call 911, even if you are not sure it is serious.
In a nutshell
The hardest stretch is usually shorter than it feels. In the best study we have, withdrawal peaked in the first week and mostly faded within two. What takes longer is refurnishing the rooms weed used to fill: the hour after work, the friend’s couch, your own bedroom.
It may take more than one try, and that is common. In one study of daily users, most attempts were short. Every day off still counts. If you keep going back, treatment is a strong next step, not a failure.
Tonight, write down your first reason and one change you will make to the room.

Stopping something that has been part of your days for a long time can leave a lot of quiet space, and some of what surfaces in it is hard. If writing some of it down would help, VentSpace is a journaling app that turns what you write into a clear read on your life balance, plus small, doable next steps. Prefer to try it on your laptop first? VentSpace Live runs in your browser, free, with nothing to install.
About this article

Written by
Sai Subramaniam
Founder, VentSpace
I write these guides because I have been where you are. I am working through my own hard seasons, and I share the things that actually helped me, so that anyone going through it has a steady companion close by instead of facing it alone. VentSpace is the app I built for exactly that: a journaling app that turns what you write into a clear read on your life balance, plus small, doable next steps toward feeling more like yourself.
This writing is honest and every claim is sourced, and it is not a substitute for professional care. If you are struggling, reaching out to a professional is a strong move, not a failure.
Explore VentSpaceTry VentSpace LiveHow this one was checked. Every factual claim traces to a named source, and the source is printed next to the claim rather than kept in a footnote. Quotes are pinned to the work they come from, with the year, the letter or the chapter where one exists. Where a widely repeated claim could not be traced, it was left out and the omission recorded. Where a figure is contested, both sides are printed.
No affiliate links, no paid placements, and nobody paid to appear here. Where we mention our own app, we say that it is ours, we state its limits, and we never position it as a substitute for care.
Reviewed: October 2026. Prices, platforms and product availability move quickly, and anything we could not verify at the time of writing is marked as unverified rather than turned into a number.
Corrections. If something here is wrong, we would rather know. Corrections are made in place, with a note saying what changed.